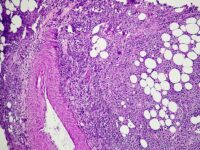
Intravesical therapy delivers treatment directly into the bladder through a urinary catheter, producing high local drug exposure while generally limiting systemic exposure. Its primary role is in non-muscle-invasive bladder cancer (NMIBC)—including carcinoma in situ (CIS), stage 0 disease, and tumors extending into the lamina propria without muscle invasion. Because these agents primarily affect the urothelium, intravesical therapy has little therapeutic role once disease has invaded deeply into the bladder wall or metastasized. Following transurethral resection of bladder tumor (TURBT), a single dose of intravesical chemotherapy is often administered within 24 hours to reduce recurrence. Subsequent treatment is determined by recurrence and progression risk; intermediate- and high-risk patients may receive an approximately six-week induction course followed by less frequent maintenance therapy for up to one year in intermediate-risk disease and three years in high-risk disease.
Bacillus Calmette-Guerin (BCG) remains the principal intravesical immunotherapy for early-stage bladder cancer. BCG induces a localized immune response against malignant urothelial cells. Expected toxicities include dysuria, urinary frequency, hematuria, fatigue, fever, chills, and other flu-like symptoms, which can persist for two to three days. For nurses, distinguishing expected inflammatory effects from potentially serious complications is particularly important. Although uncommon, systemic BCG infection can occur, especially in immunocompromised patients; a persistent high fever warrants prompt clinical evaluation.
The therapeutic landscape has expanded for BCG-unresponsive NMIBC. Nadofaragene firadenovec (Adstiladrin) is an intravesical gene therapy that uses a viral vector to introduce the gene for interferon alfa-2b into urothelial cells and is typically administered every three months. Relevant adverse effects include fatigue, bladder spasms, urinary frequency, and hematuria. Because the vector is a live virus, the ACS document notes that treatment is generally not recommended for patients with weakened immune systems. Nogapendekin alfa inbakicept (Anktiva), an IL-15 receptor agonist, is administered with BCG for NMIBC that has not responded adequately to BCG alone. It activates NK and T cells and can produce local urinary toxicities in addition to those associated with BCG.
Intravesical chemotherapy is commonly considered when BCG is ineffective or unavailable. Gemcitabine and mitomycin are used most often, with valrubicin, epirubicin, and docetaxel among other potential agents. Local bladder irritation, dysuria, and hematuria predominate because systemic exposure is generally limited, reducing many toxicities associated with intravenous chemotherapy.
The American Cancer Society’s Intravesical Therapy for Bladder Cancer also describes newer delivery approaches that extend urothelial drug exposure. The gemcitabine intravesical system (Inlexzo) remains in the bladder for approximately three weeks and can be used for BCG-unresponsive NMIBC with CIS. Nursing assessment should include urinary frequency, dysuria, UTI, cytopenias, and laboratory abnormalities. Importantly, its internal metal wire has implications for MRI, making treatment-device documentation and patient education particularly relevant. Mitomycin gel (Zusduri) converts from liquid to gel after instillation, prolonging contact with the bladder wall, and can be used for recurrent intermediate-risk NMIBC as an alternative to another TURBT; urinary obstruction, UTI, hematuria, cytopenias, and laboratory abnormalities are notable toxicities.
For oncology nurses, the major clinical implications are accurate assessment of urinary and systemic symptoms, recognition of potentially serious infection, awareness of immunocompromised status, treatment-specific toxicity monitoring, and reinforcement of increasingly complex treatment schedules. As options for BCG-unresponsive disease expand, nurses also need to distinguish therapies that may sound similar but have substantially different mechanisms—live-organism immunotherapy, viral-vector gene therapy, immune activation, conventional intravesical chemotherapy, and sustained-release drug delivery. This distinction is increasingly important when performing medication reconciliation, triaging symptoms, educating patients, and coordinating multidisciplinary care.
AI disclosure: Generative artificial intelligence (AI) was used to prepare this article. American Nurse Journal editors critically reviewed and revised the AI-generated content, verified all factual information and references, and assumes full responsibility for the accuracy, originality, and final version of the manuscript.